
Category: Tremor
Objective: To describe a tremor-dominant presentation of neuronal intranuclear inclusion disease (NIID) that initially resembled essential tremor plus (ET-plus), highlighting the need for diagnostic reconsideration in tremor syndromes accompanied by additional neurological signs.
Background: ET-plus refers to essential tremor accompanied by additional mild neurological signs such as questionable dystonia, impaired tandem gait, or mild cognitive impairment. However, the boundaries of these “soft neurological signs” are not clearly defined, and their interpretation may vary depending on the extent of clinical evaluation. In some patients, findings initially considered compatible with ET-plus may represent early manifestations of alternative neurological disorders.
Method: Clinical examination, tremor phenomenology assessment, brain magnetic resonance imaging (MRI), autonomic testing, nerve conduction studies, skin biopsy, electron microscopy, and genetic testing for GGC repeat expansion in the NOTCH2NLC gene were performed.
Results: A 71-year-old woman presented with progressive tremor involving the head and upper limbs, initially diagnosed as essential tremor. Examination revealed asymmetric tremor with resting components, dystonic finger posturing, jerky head tremor, voice tremor, and mild gait ataxia. Brain MRI demonstrated diffuse white matter hyperintensities with involvement of the U-fibers and corpus callosum. Diffusion-weighted imaging showed linear hyperintensities along the corticomedullary junction. Nerve conduction studies revealed sensorimotor polyneuropathy. Skin biopsy demonstrated intranuclear inclusions in sweat gland epithelial cells and dermal fibroblasts, and electron microscopy showed filamentous intranuclear inclusions. Genetic testing confirmed pathogenic GGC repeat expansion in the NOTCH2NLC gene, establishing the diagnosis of NIID.
Conclusion: NIID may initially present as a tremor-dominant syndrome resembling ET-plus. This case highlights that ET-plus may represent a transitional clinical label rather than a final diagnosis. Careful longitudinal evaluation and additional investigations are essential when atypical neurological features accumulate in patients with presumed ET-plus.
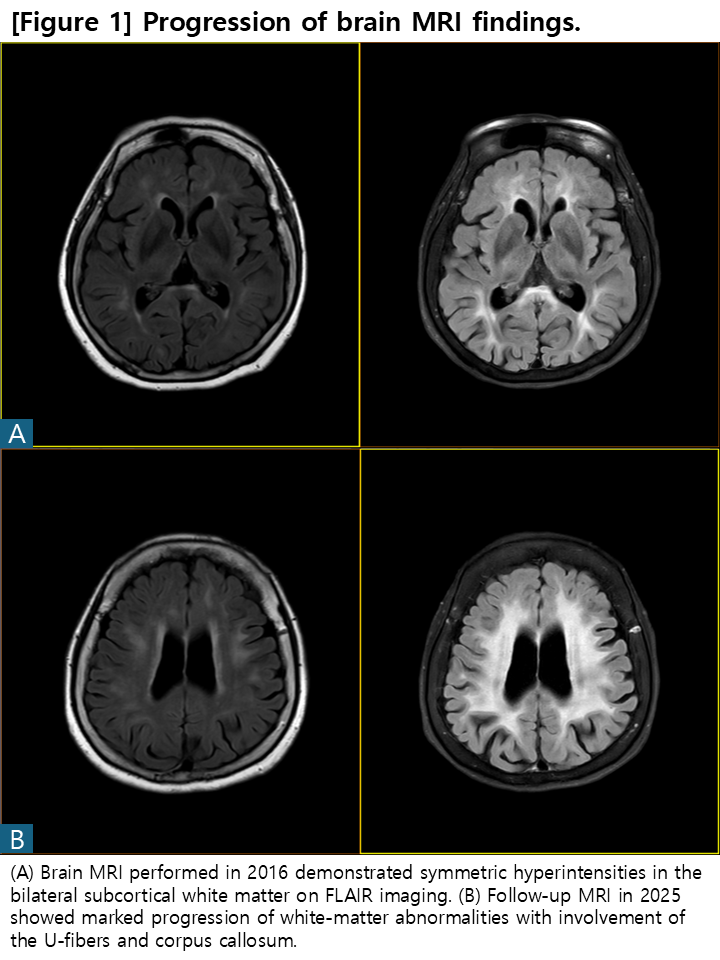
[Figure 1] Progression of brain MRI findings.
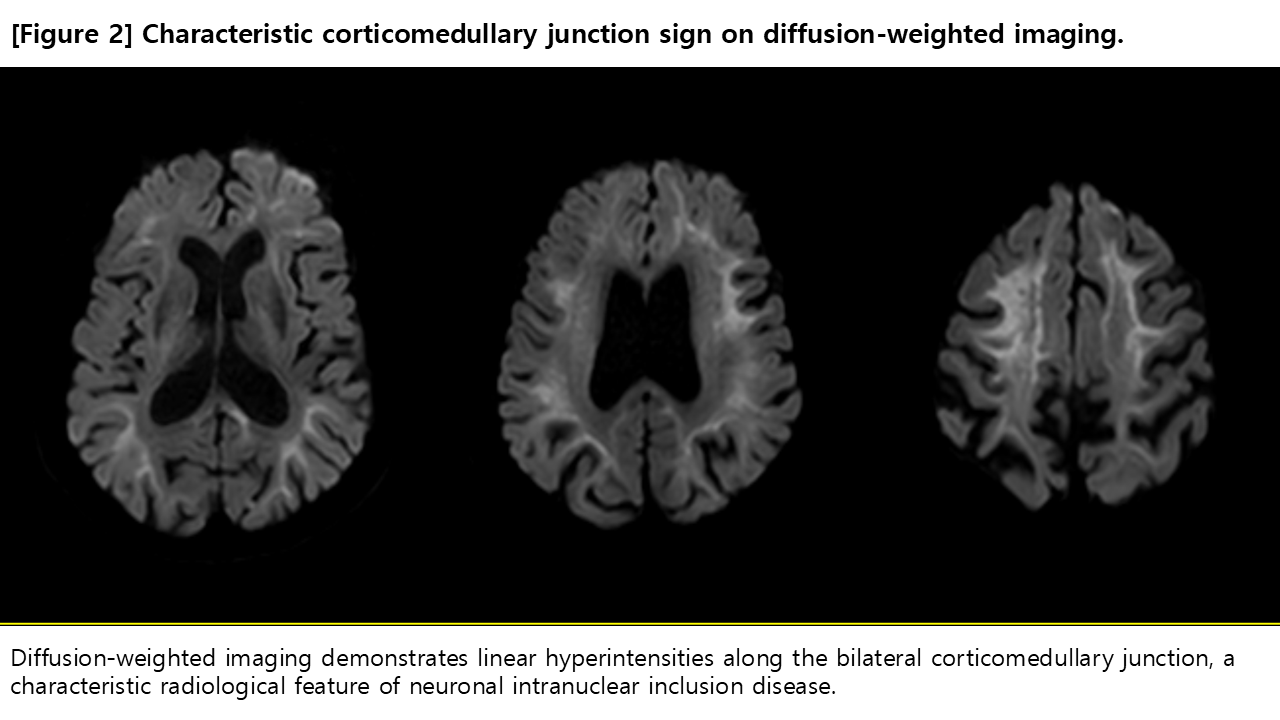
[Figure 2] Characteristics imaging sign.
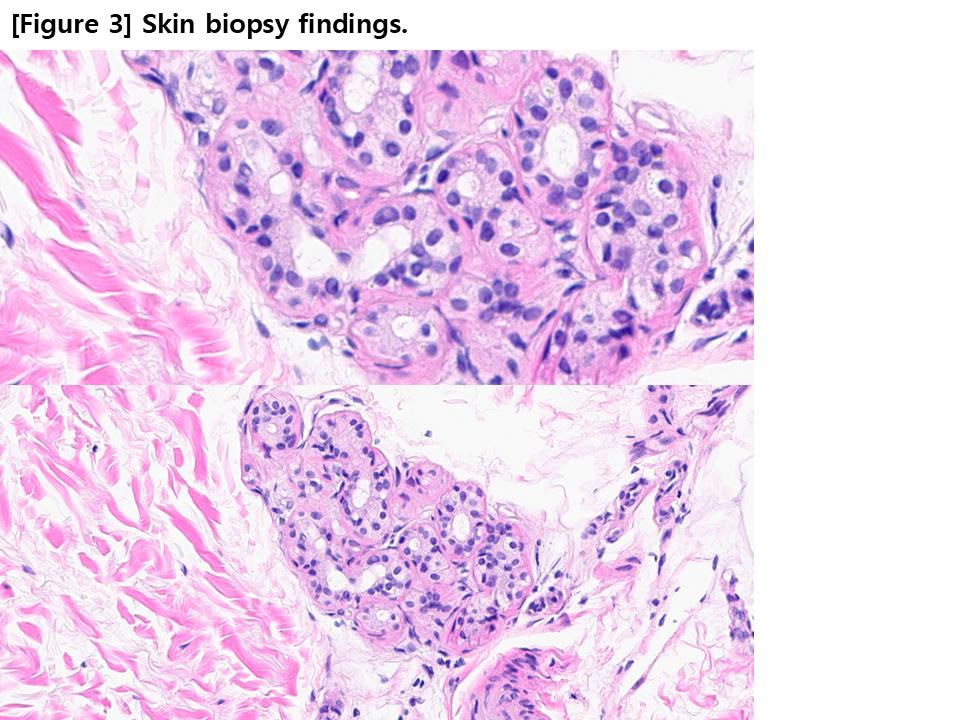
[Figure 3] Skin biopsy findings.
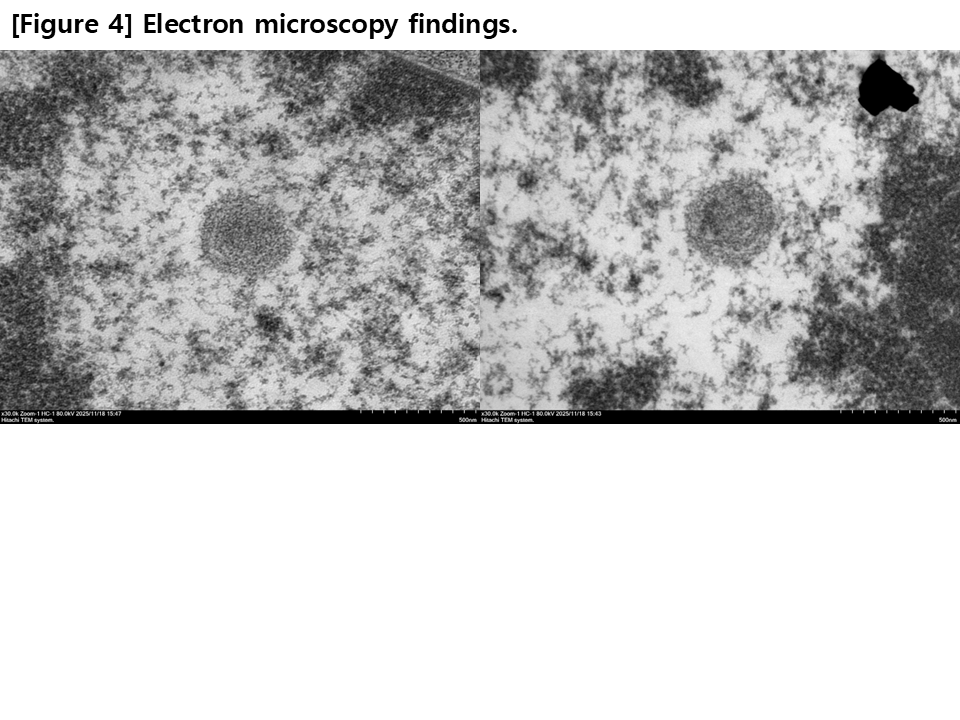
[Figure 4] Electron microscopy findings.
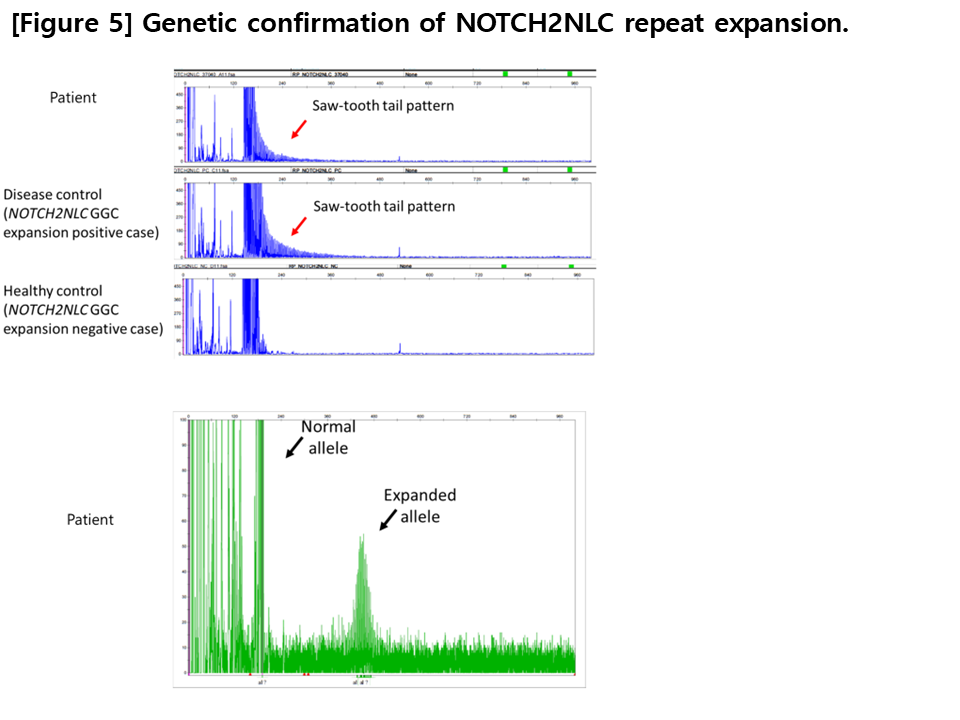
[Figure 5] Genetic confirmation.
To cite this abstract in AMA style:
H. Yang, D. Kwon. When “Essential Tremor Plus” Is Not Enough: A Tremor-Dominant Presentation of Neuronal Intranuclear Inclusion Disease [abstract]. Mov Disord. 2026; 41 (suppl 1). https://www.mdsabstracts.org/abstract/when-essential-tremor-plus-is-not-enough-a-tremor-dominant-presentation-of-neuronal-intranuclear-inclusion-disease/. Accessed October 1, 2026.« Back to 2026 International Congress
MDS Abstracts - https://www.mdsabstracts.org/abstract/when-essential-tremor-plus-is-not-enough-a-tremor-dominant-presentation-of-neuronal-intranuclear-inclusion-disease/