
Objective: Choosing the right target for deep brain stimulation surgery for dystonic tremor can be tricky. Patients usually treated by VIM-DBS or GPi-DBS. Dual targeting is rare, and often performed when first surgery did not give optimum results.
Combined VIM- and GPi-DBS, by modulating the cerebello-thalamo-cortical network and the basal ganglia-thalamo-cortical network, both involved in DT pathophysiology, may be more efficient than single DBS targeting only one of them. We also discuss programming strategies for these cases and predict which target is likely to be more beneficial based on symptomatology.
Background: Movement disorders can occur following central and peripheral nervous system trauma. Unilateral posttraumatic dystonic tremor is rare. The pathophysiology is complex. Response standard treatment is variable. There is no consensus about the best surgical targeting strategy in patients with concomitant tremor and dystonia.
Method: We discuss our experience of DBS for a patient with post traumatic tremor. we discuss the challenges in programming. we review the literature for a brief review.
Results:
A 28-year-old patient presented with right side dystonic tremor. She experienced head injury at the age of 5. She underwent surgery at right frontal region and was in ICU for nearly 6-months. She recovered slowly. At the age of 15, she started to have low amplitude tremors of the right hand. Gradually got worse and her hand became dystonic. She started writing with her left hand from the age of 16. She received Botox in her right hand for next several years. Initially she had good partial response from Botox. Subsequently he did not get any improvement with Botox. She underwent left VIM and GPI deep brain stimulation at the same setting. Patient experienced excellent benefit from the surgery. She could write with her right hand after 10 years.
Conclusion: Managing dystonic tremor is different than dystonia or tremor. Dual target DBS might have synergistic effect. The axial symptoms may respond more to GPI and peripheral symptoms may respond to VIM. This can avoid a second surgery, improve patient safety and satisfaction and overall outcome.
Part of the abstract was presented in WFNS 2025 conference
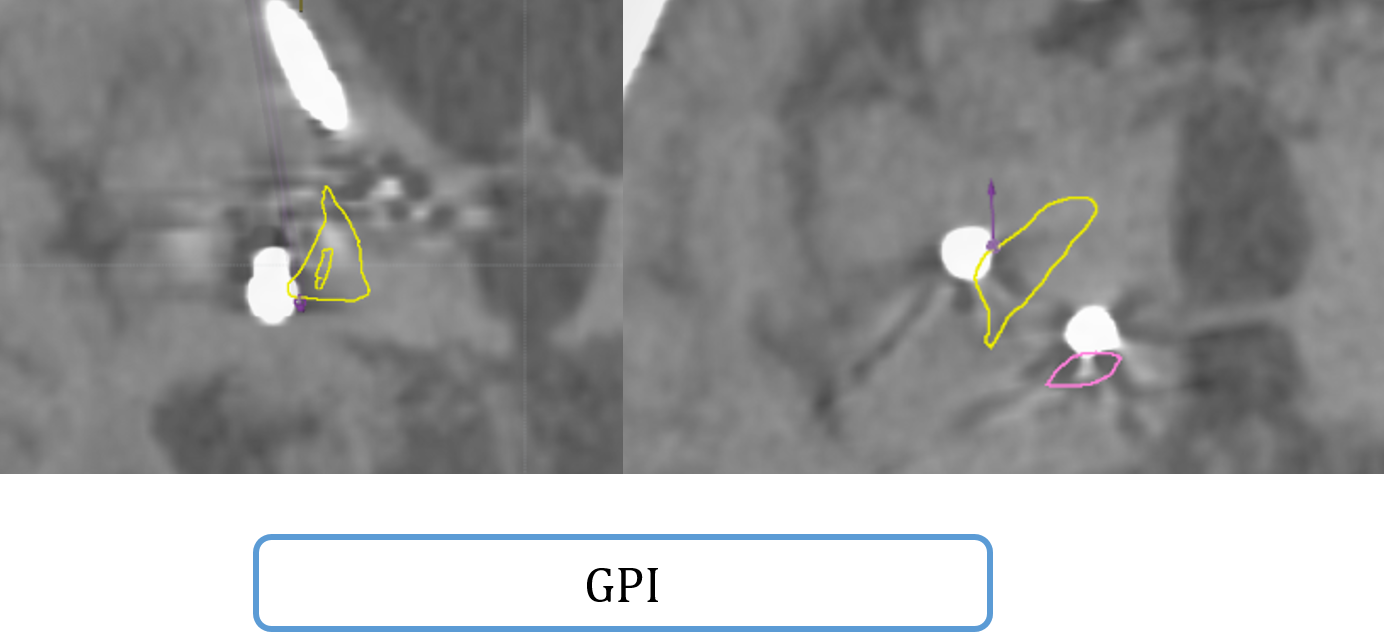
Figure 1
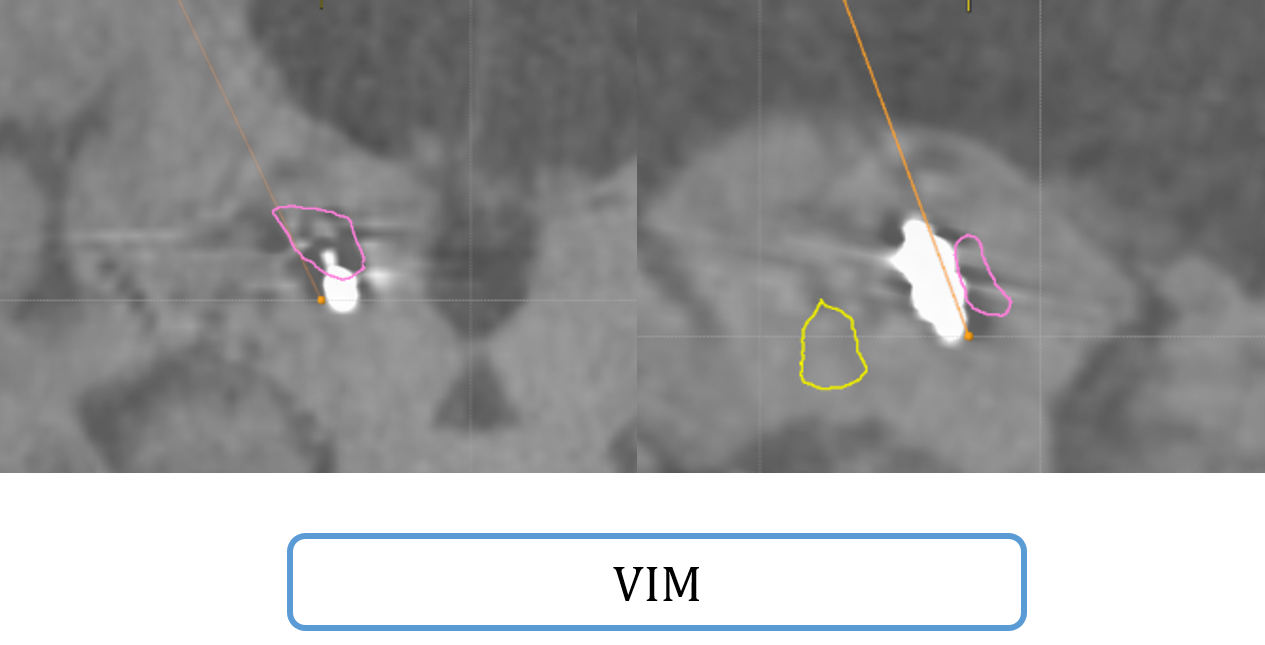
Figure 2
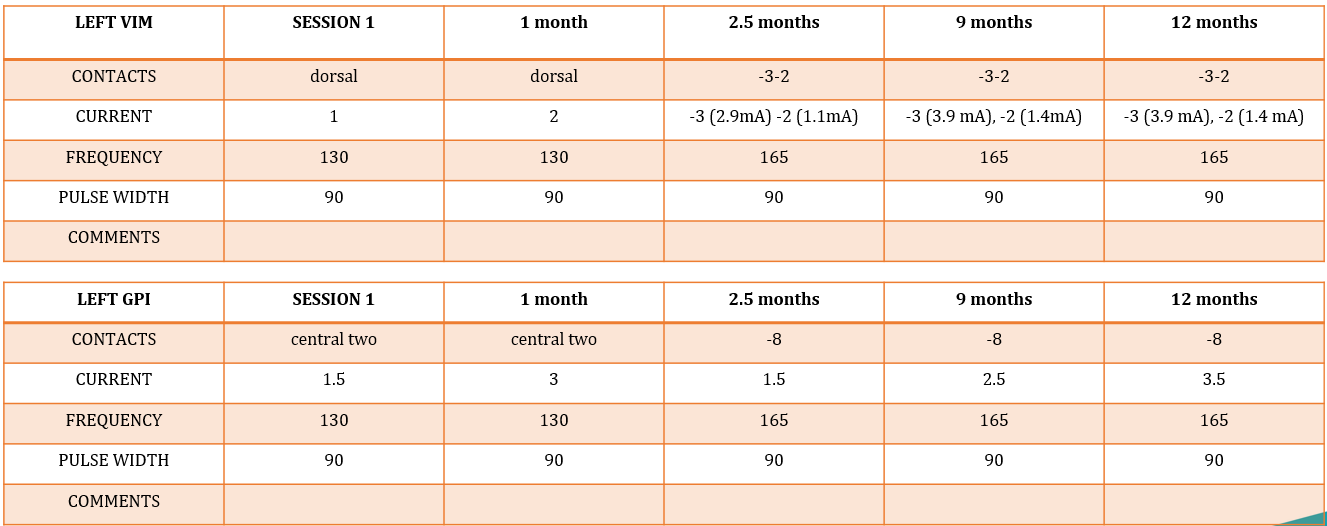
Figure 3
References: Paoli D, Mills R, Brechany U, Pavese N, Nicholson C. DBS in tremor with
dystonia: VIM, GPi or both? A review of the literature and considerations from a
single-center experience. J Neurol. 2023 Apr;270(4):2217-2229.
To cite this abstract in AMA style:
T. Maiti, C. Ugas, S. Mittal. Single stage Dual target Deep Brain Stimulation for Dystonic Tremor [abstract]. Mov Disord. 2026; 41 (suppl 1). https://www.mdsabstracts.org/abstract/single-stage-dual-target-deep-brain-stimulation-for-dystonic-tremor/. Accessed October 1, 2026.« Back to 2026 International Congress
MDS Abstracts - https://www.mdsabstracts.org/abstract/single-stage-dual-target-deep-brain-stimulation-for-dystonic-tremor/