
Objective: To characterize clustering patterns of sleep disorders in multiple system atrophy (MSA) and evaluate their clinical impact.
Background: Sleep disorders are common in MSA. However, how different sleep disorders cluster and relate to clinical impact remains unclear.
Method: We analyzed 189 patients with MSA (MSA-P:128; MSA-C:61), including 46 with longitudinal follow-up. Sleep disorders were assessed by PDSS-2, Epworth Sleepiness Scale, RBD-HK questionnaire (≥19 indicating probable RBD), and apnea–hypopnea index (AHI) and oxygen desaturation index (ODI). Clinical measures included MDS-UPDRS III, UMSARS, PDQ-39, SCOPA-AUT, and cognition. Multivariable regression models evaluated associations of sleep disorders with clinical variables, and longitudinal effects were examined using linear mixed-effects models. Pairwise comorbidity analysis and principal component analysis (PCA) were performed for interactions and composite sleep burden.
Results: Sleep disorders were highly prevalent and frequently clustered (Figure 1). Probable RBD occurred in 72.4% of patients, nocturnal hypoxia in 71.2%, PD-related sleep disorder in 65.7%, obstructive sleep apnea in 63.3%, and excessive daytime sleepiness in 29.7%. More than half of patients had two or more coexisting sleep abnormalities, reaching 83.33% among those with follow-up. Distinct sleep disorders showed differential clinical associations. Overall, PDSS-defined sleep disorder was the strongest predictor of poorer quality of life (β=1.51). Greater RBD severity was associated with gastrointestinal (β=0.11) and urinary autonomic dysfunction (β=0.09) (Figure 2). In MSA-C subtype, sleep-related breathing indicators were mainly linked to depressive symptoms. Longitudinal analyses showed that higher PDSS scores predicted worsening PDQ-39 over time (β=1.61) (Figure 3). Comorbidity analyses revealed synergistic effects of sleep disorders: patients with both RBD and PDSS abnormalities had markedly worse quality of life (β=39.03) and more severe gastrointestinal symptoms (β=6.00) (Figure 4). PCA identified a respiratory-dominant sleep burden component driven by AHI and ODI, significantly associated with poorer quality of life (β=7.14) (Figure 5).
Conclusion: Different types of sleep disorders are closely associated with clinical heterogeneity and MSA subtypes. Coexisting sleep disorders exert synergistic effects, leading to poorer quality of life.
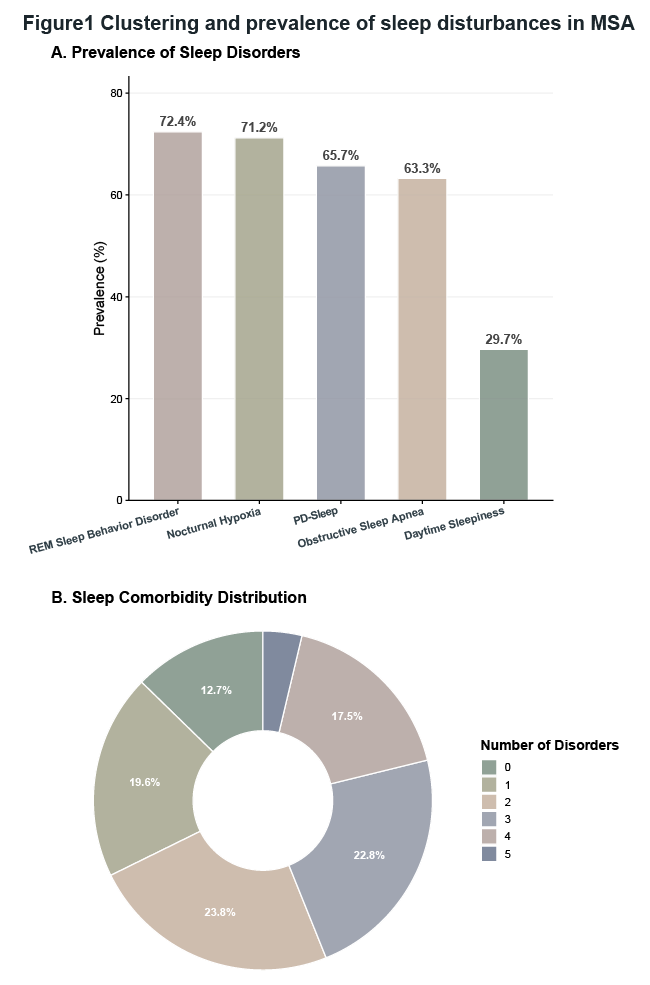
Figure1
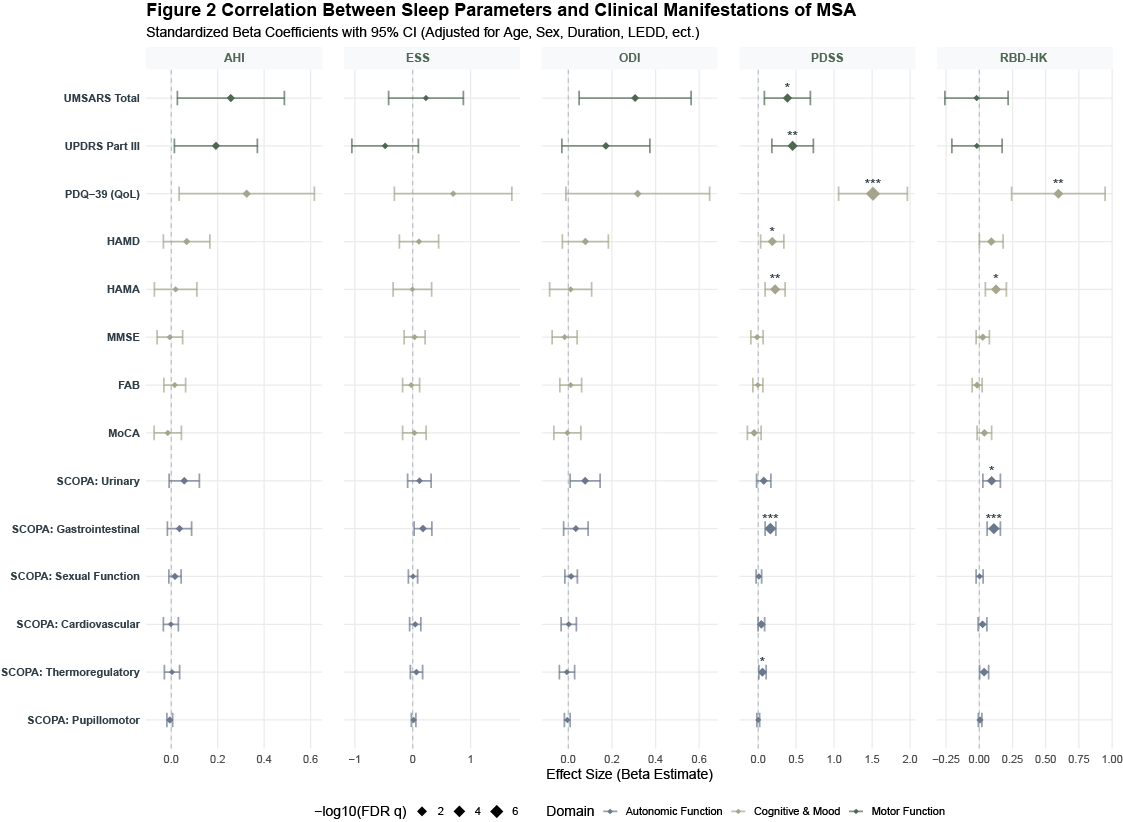
Figure 2
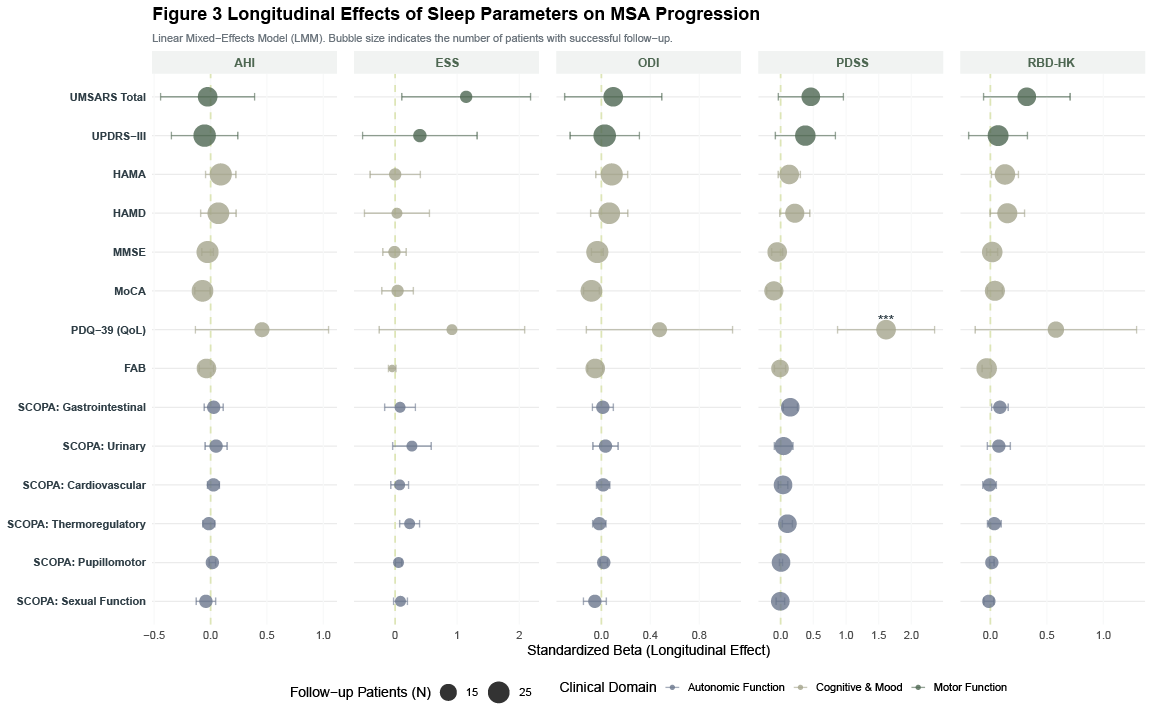
Figure 3
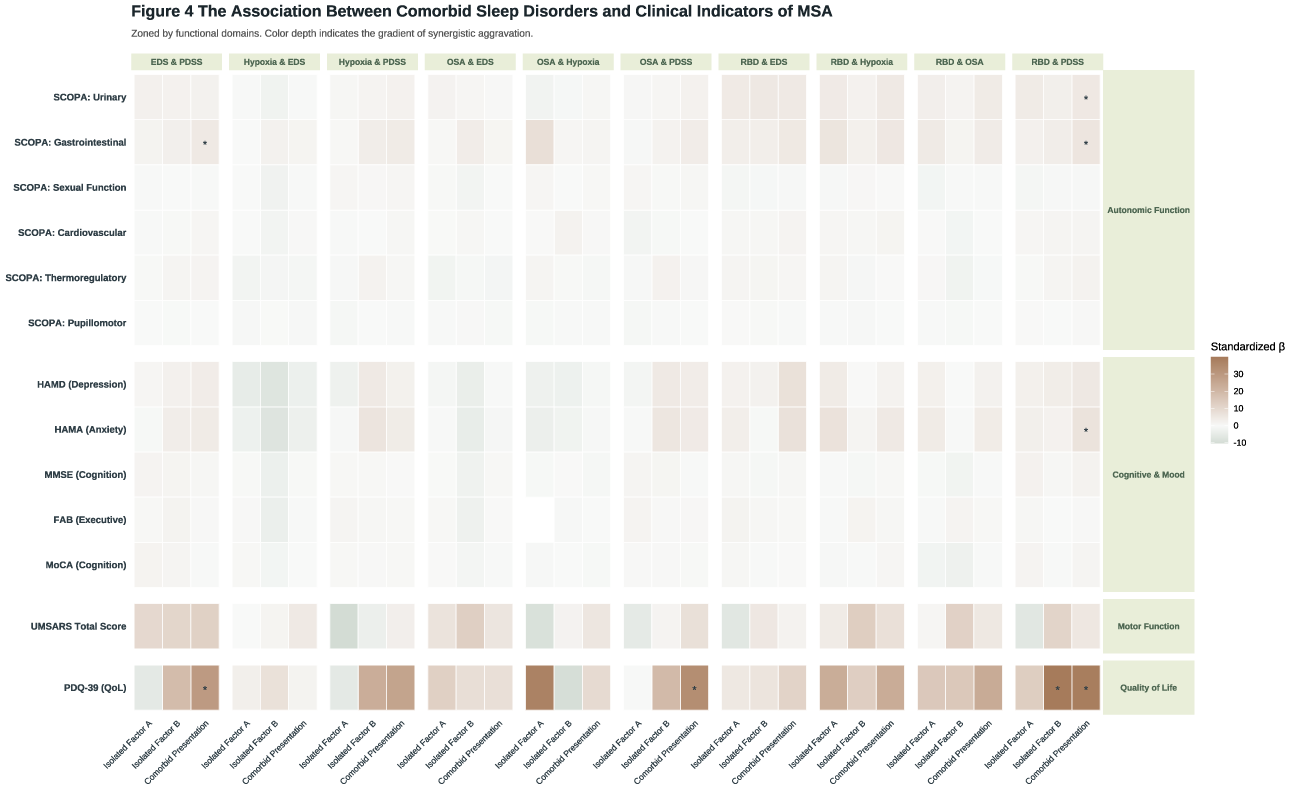
Figure 4
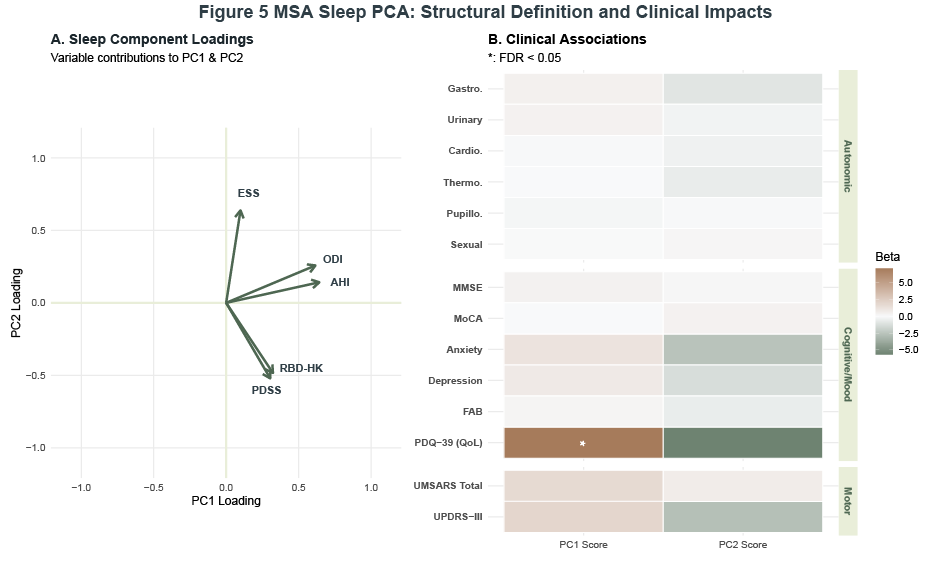
Figure 5
To cite this abstract in AMA style:
D. Dong, L. Li, L. Luo, W. Wang. Sleep disorder Clustering and Clinical Impact in Multiple System Atrophy [abstract]. Mov Disord. 2026; 41 (suppl 1). https://www.mdsabstracts.org/abstract/sleep-disorder-clustering-and-clinical-impact-in-multiple-system-atrophy/. Accessed October 1, 2026.« Back to 2026 International Congress
MDS Abstracts - https://www.mdsabstracts.org/abstract/sleep-disorder-clustering-and-clinical-impact-in-multiple-system-atrophy/